
A long term patient with a long forensic hx but now on a back-ward was on two cigarettes a day. (That’s harmful in itself because the patient’s nicotine addiction is not being satisfied. That’s another story.) He demanded another when he’d already smoked them both. Told ‘no’, he attacked the female nurse, got on top of her, was punching her in the face. After the fight was brought to an end, (not telling you how) the pt was not secluded! Even worse, the ward manager and service manager allowed the pt to smoke on the ward. The female nurse has broken ribs and teeth.
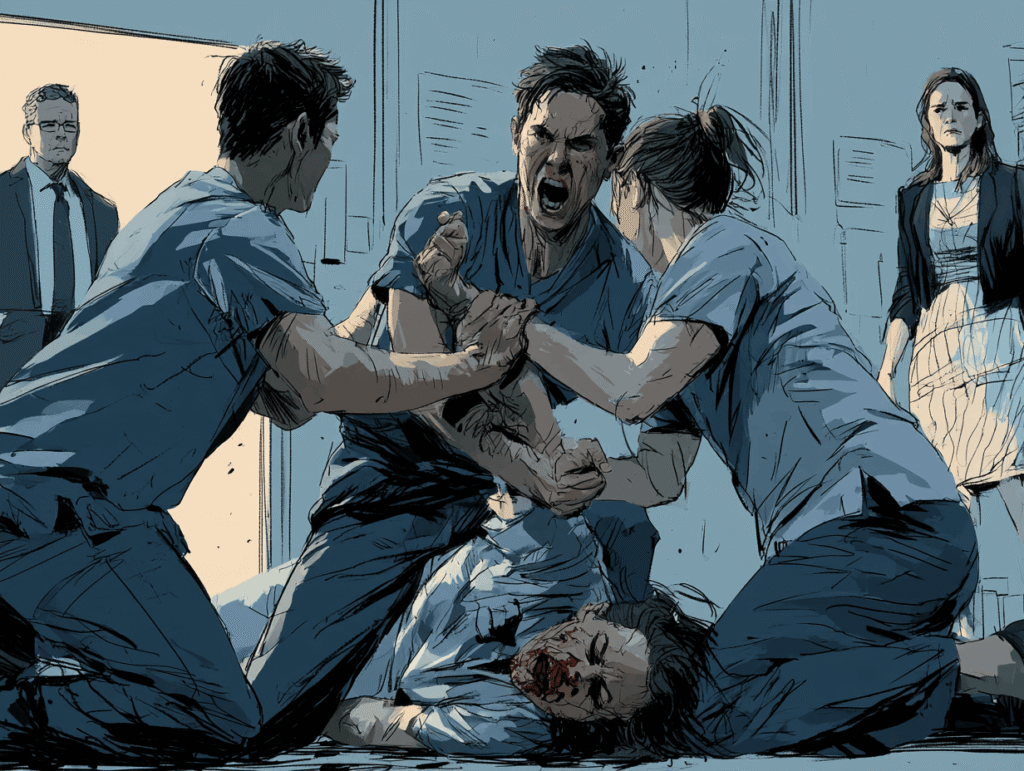
Next day, this scrote is gladhanding and back-slapping those managers and everyone else who is stupid, cowardly or gaslit enough to go along with it and shake the Richard the 3rd’s hand.
Let me tell you what is going on under the surface.
1) Those professionals are not maintaining correct professional and moral boundaries. These are powerful pieces of armour, if not weapons, in the fight to keep the ward safe, moral and therapeutic. Their beauty is in their non-confrontational and non-coercive nature. (Some of them are anyway. Others involve saying ‘no’ a lot and meaning it.) It is our duty to maintain the boundaries. A boundary-less ward quickly descends into chaos and becomes the playground of ASPDs and psychopaths. Genuinely ill patients can forget about any hope of recovery.
NB pushing and testing one’s boundaries isn’t one of the diagnostic criteria for ASPD’s but it probably should be.
NNB Managers, government and those pesky supra-national bodies are actively engaged in the fight against maintaining boundaries. More on that another day.
2) Shunning the wrongdoer has been ducked. Instead of forcing the violent patient to serve an uncomfortable period of being shunned, i.e. given the cold shoulder, (*) weak staff have chickened out and granted him absolution. When shunning is done properly, every attempt by the patient to be chummy and jokey with you (and thereby pretend nothing – or nothing serious – happened), gets nothing but ice and frost. It works as reinforcement of the expected higher standards he had better rise to in future.
3) He has manipulated the weak staff into taking a side. His side. There are only two sides here, good and evil. The battered nurse is on the side of good. The scrote is on the opposite. Taking the scrote’s side means not taking his victim’s. By being too weak to refuse to shake his hand, to fail to remind him over the coming days and weeks about the battering he gave her, to challenge him over the shame he should be feeling, to ask him what action are you taking to address your selfishness, violence, entitlement etc she is being invalidated and her suffering trivialised. I may have mentioned before how psychopaths absolutely cream their panties when they manipulate weak people to (usually reluctantly) side with them. It’s overcoming the reluctance makes it a victory. How many nights is the wretch rubbing one out, re-running in his poisoned mind how he deceived and played you into renouncing your colleague and thrilling at the extra pain that will cause her.
4) What you do, if you’re a moral, upstanding, professional nurse. You have and maintain a firm moral compass. You don’t make friends with any patient and especially not PDs and psychopaths. Never fold. Assume everything this type of patient tries is manipulation and testing. Act as a role model and show the weaker patients and the ill patients there is someone who’ll stand up for them.
*) It’s not hard. When you are part of a solid staff team, it’s easy. We used to do this after unlocking a staff-attacker from seclusion. Show them at every encounter, e.g. tablets, mealtimes, formal events like ward round, that normal service has not returned, that they must serve a community sentence, must show (and if possible, express) remorse before they get normal service back. Do no favours. Give the bare minimum. You’ll know when enough’s enough.
NB not all staff-attackers are bad or PD. Plenty are capable of remorse and shame and this approach is helping them face up to changes they need to make.
Continues in The state of play you are paying for Pt 3b
Leave a Reply